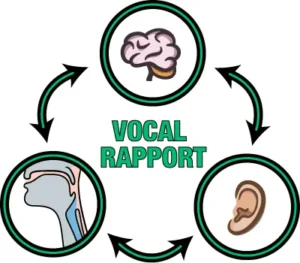
Vocal Self-Rapport
Vocal Self-Rapport is the ability to relate to one’s voice and to hear and experience it insightfully. It includes being self-aware of pitch, effort level, quality, loudness, etc. Accomplished singers may have exquisite vocal self-rapport, being able to match pitch and be aware of vowel color, larynx position in the neck, and other kinesthetic feedback.
At the other end of the spectrum, a small percentage of individuals have remarkably limited vocal self-rapport. Such individuals may not be able to match pitch. In addition, they may not even perceive the difference between an upward and downward vocal siren.
For a clinician, assessing the vocal capabilities of a patient without vocal self-rapport can be difficult, because such a patient may not be able to respond correctly to elicited vocal tasks which could otherwise reveal vocal limitations or aberrations. Furthermore, it can be difficult for a speech/voice therapist to shape or modify inappropriate voice production because, though the patient’s hearing may be normal, he or she may yet struggle to “hear” with any insight. That is, the patient can struggle to understand what is being asked of them during speech therapy, or to identify whether or not changes he or she makes to voice production are on target.
Audio Examples of Poor Vocal Rapport
Poor Rapport in Vocal Capability Battery
This man has minimal awareness of, and connection with his voice’s capabilities.Matching Pitch
This man has better access to (rapport with) his upper voice, but is unable to match pitch.
Upper Voice
This woman doesn’t match pitch, but more importantly, can’t “find” or “access” upper voice. This is not a lack of vocal capability, but instead lack of vocal rapport.
Increasing Loudness
This man has poor rapport with increasing loudness

Share this article
Vocal Rapport is Crucial for Evaluation of Voice
An ability called “rapport with one’s voice” is essential for becoming a skilled singer, mimic, ventriloquist, or impressionist. This skill—an ear-brain-larynx connection—not only allows individuals to reproduce or approximate vocal sounds, but also enables voice experts and clinicians to model and elicit a wide range of vocal tasks. Likewise, when this ability is present in a student or patient, it allows them to respond effectively by matching or approximating those tasks.
In this video, Dr. Bastian explores the critical role of vocal rapport in evaluating voice disorders. Drawing from examples in his laryngology practice, he illustrates both strong and weak rapport and how this impacts the diagnostic process. Vocal rapport is also a foundational element for both clinician and patient in Part 2 of Bastian’s “Integrative Diagnostic Model.” When this ability is lacking in either, the insights gained from Part 2 may be more difficult to obtain.
Vocal Rapport Inventory for Evaluating Voice Disorders
In Dr. Bastian’s Integrative Diagnostic Model for voice disorders, clinicians triangulate and integrate information from three essential sources:
- A skillful History (10 or 15 minutes)
- A Vocal Capability Battery (VCB) that evaluates vocal capabilities, limitations, and aberrations (2 or 3 minutes), and
- A magnified, close-range Laryngeal Examination (15 minutes).
Part 2—the VCB that can provide crucial information—depends heavily on bi-directional vocal rapport between clinician and patient. In this video, Dr. Bastian explains why vocal rapport (which can be enhanced with proper training) is essential to accurate diagnosis, and how poor vocal rapport can impede the diagnostic process.
What Is Vocal Rapport and What Is Its Role in Voice Diagnosis?
Voice clinicians need vocal rapport to elicit different vocal tasks from patients and to understand what the patient produces in response. Ideally, patients also have sufficient vocal rapport to be able to recognize a particular vocal pitch, sound quality, or loudness demonstrated by the clinician and to direct his or her voice toward producing it.
In this video, I explain vocal rapport more fully and illustrate its important role in voice diagnosis with four patient examples.
